

what is mini facelift surgery
Understanding what is mini facelift surgery starts with anatomy rather than marketing language. A Mini Facelift is a focused operation for early to moderate laxity in the lower face, using carefully planned incisions and, when appropriate, support of the superficial musculoaponeurotic system, or SMAS. It is not simply excess skin removal or a smaller version of every step performed during a comprehensive facelift.
Key Takeaways
- A mini facelift addresses early to moderate sagging in the lower face through precise surgical techniques rather than generalized tightening.
- Supporting the SMAS layer is a key component of the procedure, distinguishing it from simpler skin-only lifts.
- Ideal candidates have noticeable but not advanced aging changes, making this operation a targeted rather than comprehensive solution.
- Incisions are carefully placed to minimize visible scarring while still providing meaningful correction of jowls and jawline laxity.
- Real costs reflect the focused nature of the surgery, which is typically less extensive than a full facelift but still requires specialized surgical skill.
The Mini Facelift offered through Albert Plastic Surgery is planned around skin quality, facial structure, degree of jowling, hairline, ear anatomy, and neck laxity. Dr. Mark Albert uses consultation and direct examination to determine whether a limited approach can address the patient’s concerns without creating an artificial, windblown appearance.
A mini facelift usually repositions or supports tissues in the lower cheeks, jowls, and jawline through shorter incisions around the ear. The procedure may involve the SMAS layer rather than relying only on skin tension. Its reach is more limited than a full facelift, particularly when loose neck skin, platysma banding, or substantial submental fullness is present. Candidacy, anesthesia, incision design, and expected healing require an in-person assessment with a qualified plastic surgeon.
What Is a Mini Facelift? Anatomical Scope and Surgical Technique
Defining the Mini Facelift: Targeted Lower Face Rejuvenation
When patients ask what is mini facelift surgery, the most useful answer is that it is a limited facelift for selected signs of facial descent. The principal treatment area is the lower third of the face, including early jowls, laxity along the mandibular border, and mild-to-moderate looseness in the lower cheek. It does not erase every sign of aging or recreate the broad tissue repositioning of a comprehensive facelift.
The surgeon releases and repositions selected tissues through individualized dissection. Some patients may receive local anesthesia and sedation, while others require a different plan based on health history, surgical extent, and facility protocols. Operative time, monitoring, bruising, swelling, and scar maturation vary by patient.
SMAS Manipulation vs. Skin-Only Tension: Why the Difference Matters
The SMAS is a fibrous layer beneath the skin and fat that connects with facial muscles and supporting structures. Addressing it can place support beneath the skin instead of asking the skin alone to hold the correction. Skin-only tightening may create excessive incision tension, a pulled appearance, or distorted ear contour when underlying laxity is not addressed.
SMAS work does not make a mini facelift identical to a deep plane facelift. Depth, direction, and tissue release differ by technique and anatomy. The surgeon should explain which layer will be treated, which areas remain outside the operative field, and how those choices affect longevity, movement, facial expression, and residual laxity.
Incision Architecture: Preauricular Lines and Hairline Preservation
Typical mini facelift incisions begin near the natural crease in front of the ear, called the preauricular fold. Depending on anatomy and the planned lift, the incision may continue around the earlobe and a short distance behind the ear. The design should follow natural shadows and avoid unnecessary tension. Hairline preservation matters because shifting the sideburn or distorting hair-bearing skin can make a scar more visible.
Scar quality depends on skin biology, closure technique, tension, sun exposure, and aftercare. Incisions may appear pink, firm, or uneven during early healing before maturing. Consultation should cover tragus shape, earlobe attachment, sideburn position, and the possibility that scars remain detectable on close inspection even when difficult to see at conversational distance.
Target Zones: Jowls, Lower Cheeks, and the Jawline
The strongest effect is usually along the lower cheek and mandibular border. Repositioning descended cheek tissue can soften the transition into a jowl and improve jawline definition. Results depend on bone structure, skin elasticity, facial volume, fat distribution, and ligamentous laxity. A mini facelift cannot reliably correct upper-face aging, deep wrinkles caused by skin quality, or every lower-face contour concern.
| Feature | Mini Facelift | Comprehensive Facelift |
|---|---|---|
| Primary reach | Lower cheeks, early jowls, and jawline | Broader lower-face correction, often including more extensive neck treatment |
| Incision pattern | Usually shorter incisions around the ear | May extend farther behind the ear and into the scalp, depending on anatomy |
| Structural work | Selected SMAS tightening or repositioning when indicated | More extensive tissue release and repositioning may be appropriate |
| Best suited to | Early or moderate lower-face laxity | More advanced facial and neck laxity requiring broader correction |
Does a Mini Facelift Address the Neck? Understanding Limitations
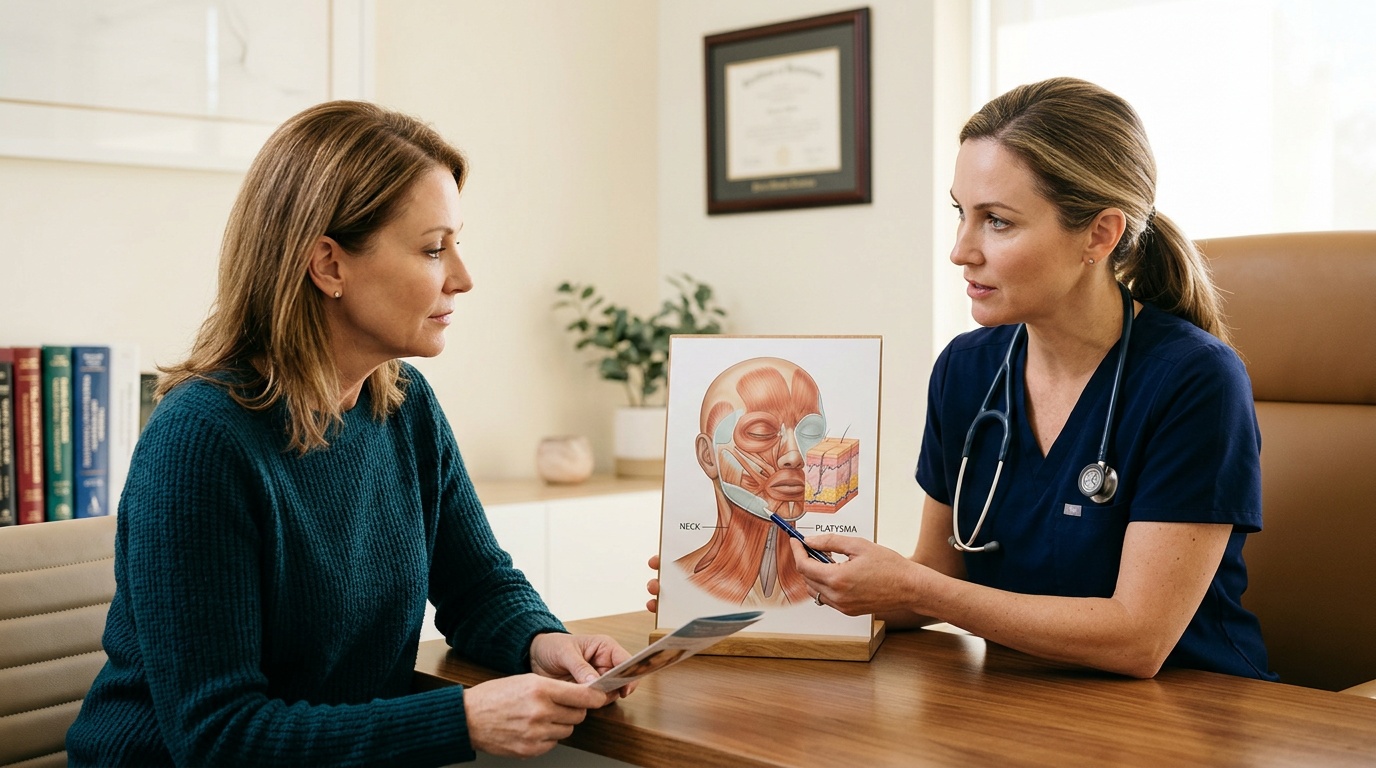
Neck Laxity and Platysma Involvement: What a Mini Lift Can and Cannot Do
A mini facelift may improve the upper neck and jawline when looseness is mild and closely connected to lower-face descent. It is not a complete neck operation. The platysma is a thin sheet of muscle extending across the lower face and neck. Vertical platysma bands, loose skin beneath the chin, and significant submental fullness may extend beyond a limited facelift’s reach.
The answer to “does a mini facelift include the neck?” varies by patient because operative field, tissue release, and incision design determine coverage. A stronger jawline does not necessarily remove visible neck bands or tighten every fold beneath the chin.
When a Separate Neck Lift Is Required
A broader neck procedure may be discussed for substantial loose skin, marked platysma separation or banding, or laxity extending well below the jaw. A different facelift design may be recommended when the neck and lower face have aged together. The plan depends on direct examination, not age alone or photographs viewed online.
Ideal Candidacy: Early Jowling in Patients in Their 40s Without Overpromising
Being in the early 40s does not automatically make someone too young for facial surgery. Some adults develop early jowling because of genetics, skin elasticity, facial proportions, weight changes, or sun exposure. A person with good skin quality and localized lower-face laxity may be considered for a focused approach after evaluation.
Medical history, smoking status, medications, healing factors, facial asymmetry, and willingness to follow postoperative instructions also matter. The goal is proportionate improvement with preserved expression, not an artificially tight face. Dr. Mark G. Albert, MD, FACS, is certified by the American Board of Plastic Surgery and is a Fellow of the American College of Surgeons; a consultation with him can determine whether a Mini Facelift matches the patient’s anatomy and goals.
Recovery Milestones: What Day 5 Really Looks Like
Day 5 after a Mini Facelift is a transition point, not the end of healing. Swelling may be settling, while bruising, tightness, mild asymmetry, and visible incision lines remain. Online photographs labeled “mini facelift pictures after 5 days” show one person’s experience, not a standard milestone. Healing varies with surgical extent, skin characteristics, medications, medical history, and individual bleeding or swelling tendencies.
Swelling Distribution and Bruising Timeline at Day 5
Swelling commonly remains near the cheeks, jawline, and ears. Bruising may be yellow, purple, or green and can extend onto the neck. One side may appear more swollen than the other. Sudden swelling, expanding bruising, severe pain, fever, drainage, or a change in skin color requires prompt contact with the surgical team.
- Days 1 to 2: Swelling and tightness are often most noticeable. Rest, head elevation, wound observation, and the surgeon’s instructions guide early care.
- Days 3 to 5: Bruising may become more apparent as swelling shifts. The face can look uneven, and incisions may still be pink or firm.
- Days 5 to 7: Preauricular sutures may be removed when the surgeon confirms adequate initial healing. This timing is commonly within five to seven days, though it varies.
- Days 7 to 10: Many patients begin returning to public activities, while residual swelling and discoloration may still be visible.
Suture Status and Incision Hygiene: What to Expect
The surgeon evaluates incision edges, skin color, drainage, tenderness, earlobe, and tragus at follow-up. Sutures may be removed in stages. Patients should keep incisions clean according to written instructions, avoid picking at crusts, and use only products approved by the surgical team. Hair washing, ointment, and showering instructions differ according to closure materials and operative details.
Pinkness, firmness, numbness, itching, and pulling may occur during scar maturation. A healing incision should not be judged by a day 5 photograph. Medical advice is needed if the wound separates, develops worsening redness, produces foul drainage, or becomes increasingly painful.
Activity Restrictions and Return to Daily Life
Walking is often introduced gradually, while strenuous exercise, heavy lifting, bending, and activities that raise blood pressure may remain restricted until clearance. Sleeping with the head elevated can help manage swelling when recommended. Driving, work, social events, and air travel depend on alertness, medication use, mobility, incision status, and the surgeon’s instructions.
Mini Facelift Cost Breakdown: Surgeon Fee, Facility, and Anesthesia
Understanding the Variables: Surgeon Fee, Facility Costs, and Anesthesia
The quoted price may include separate charges. The surgeon’s fee covers consultation, planning, surgical skill, and the procedure. Facility costs can cover the operating room, nursing staff, sterile supplies, recovery monitoring, and postoperative support. Anesthesia charges depend on whether the operation uses local anesthesia with sedation or another plan. Research findings commonly place mini facelift operative time at approximately 60 to 90 minutes with local anesthesia and sedation, while a comprehensive facelift may require three to five hours under general anesthesia. The actual plan is individualized.
Ask for an itemized estimate. Confirm whether consultation, testing, garments, prescriptions, follow-up visits, revision-related care, and unexpected overnight observation are included. Dr. Mark Albert can explain which portions relate to planned anatomy and which costs are determined by the facility or anesthesia provider.
Mini Facelift vs. Full Facelift: Realistic Cost Comparisons in New York and Nationwide
National pricing data commonly places mini facelift procedural fees between $7,000 and $12,000. Comprehensive deep plane or full facelifts addressing broader facial and neck laxity commonly range from $15,000 to more than $30,000 in major metropolitan markets such as New York City. These are general ranges, not a personal quote. Location, surgeon experience, complexity, anesthesia, facility selection, and neck treatment can shift the total.
| Cost factor | Mini Facelift | Comprehensive facelift |
|---|---|---|
| Typical scope | Selected lower-face lifting with shorter operative reach | Broader facial correction, often with more extensive neck treatment |
| Reported procedural fee range | Approximately $7,000 to $12,000 nationally | Approximately $15,000 to more than $30,000 in major metropolitan markets |
| Main cost drivers | Surgeon, facility, anesthesia, and limited operative extent | Longer surgery, broader dissection, anesthesia, facility, and neck correction |
| Meaning of a lower quote | May reflect narrower scope or excluded fees | May reflect a limited plan rather than full correction |
Hidden Costs and Financing Considerations
A lower advertised price may exclude anesthesia, facility charges, supplies, testing, or follow-up care. Patients comparing “mini facelift cost near me” should compare complete estimates in the same geographic area. Ask whether the plan includes neck treatment, how revisions are handled, and which expenses remain the patient’s responsibility if healing requires additional evaluation.
Financing may divide payments over time but does not change surgical risks, recovery requirements, or total contractual obligation. Review interest, administrative fees, cancellation terms, and payment timing before signing. Elective facelift surgery should be planned around medical readiness and realistic expectations. Consultation is the appropriate setting to discuss candidacy, technique, total cost, and the limitations of a focused lift.
How to Evaluate Mini Facelift Results and Common Questions

When reviewing what is mini facelift surgery results, look beyond dramatic changes in one photograph. A useful gallery shows comparable images before surgery and after healing, with consistent lighting, camera distance, expression, and head position. “Mini facelift before and after pictures” can illustrate a surgeon’s approach but cannot predict an individual outcome. Dr. Mark Albert’s consultation process assesses facial structure, skin quality, tissue descent, scar placement, and the desired degree of change.
Assessing Before-and-After Photos: Lighting, Angles, and Anatomical Markers
Compare the jawline, lower cheek, jowl transition, and symmetry rather than focusing only on smooth skin. Shadows and head position can conceal laxity or alter apparent ear position. Look for patients with similar anatomy, and ask whether images show early healing or mature results. Review should include the limits of correction, not only visible improvement.
- Match the camera angle, facial expression, lighting, and distance between photographs.
- Examine the mandibular border and jowl area from front and oblique views.
- Check whether the ear, sideburn, and hairline retain a natural position.
- Ask how long after surgery each image was taken and whether the result is fully healed.
- Discuss which concerns remain outside the procedure’s anatomic reach.
Earlobe Shape and Tragus Position: Signs of a Natural Result
The earlobe should maintain natural size, contour, and attachment rather than appearing pulled downward or forward. The tragus, the small cartilage structure at the ear’s entrance, should remain proportionate and not look flattened or excessively exposed. Preauricular scars may be visible on close inspection while pink or firm, but their placement should follow natural creases without conspicuous tension.
Questions about scarring, ear anatomy, residual neck laxity, and final photographs belong in consultation with a qualified plastic surgeon. Candidacy, technique, healing, risks, and outcomes vary by patient and cannot be established from an online gallery alone.
Frequently Asked Questions
How long will a mini facelift last?
A mini facelift may provide improvement for several years, but the duration varies with skin quality, aging, facial structure, lifestyle, and surgical technique. Mini facelift results continue to change as natural aging progresses, and the procedure does not stop future laxity. Dr. Mark Albert can discuss expected durability during an individual examination.
How expensive is a mini facelift?
Mini facelift cost varies according to surgical technique, anesthesia, facility fees, geographic location, and whether related procedures are included. A personalized estimate requires a consultation because the recommended operation and extent of tissue work differ among patients. Patients should also ask which services are included in the quoted fee and which may be separate.
What is the downside of a mini facelift?
A mini facelift may provide less correction and shorter durability than a comprehensive facelift, particularly when significant neck laxity, platysma banding, or loose skin is present. Possible risks include bleeding, infection, scarring, temporary numbness, asymmetry, hairline or ear distortion, and changes that may require further treatment. Individual risks should be reviewed with a qualified plastic surgeon.
Which is better for me, a neck lift or a mini facelift?
A mini facelift generally suits early to moderate laxity in the lower cheeks, jowls, and jawline, while a neck lift may be more appropriate for substantial loose skin, neck bands, or fullness beneath the chin. Some patients may need a combined or broader plan. Dr. Mark Albert determines the appropriate option through examination, medical history, and discussion of goals.
What is the new facelift everyone is getting?
There is no single new facelift that is appropriate for everyone, although terms such as mini facelift and deep plane facelift are often used in marketing and online searches. A deep plane facelift involves a different level of tissue release than a mini facelift and may address broader facial descent. Technique selection depends on anatomy, laxity, goals, and clinical assessment.
Can a mini facelift be combined with other facial procedures?
A mini facelift can sometimes be combined with procedures that address concerns outside the lower face, such as volume changes, eyelid aging, or skin texture. The appropriate combination depends on health history, anatomy, operative scope, and anesthesia planning. Combining procedures may also affect risks, cost, and healing, so the full plan requires an individualized consultation.

